

Thiazide diuretics are a major class of diuretic medications commonly associated with hypertension management and mild fluid retention. They help the kidneys remove more sodium and water through urine, which can reduce fluid volume and support blood pressure control when used as prescribed. Nursing and healthcare students need to understand thiazides because they connect kidney function, sodium handling, blood pressure, fluid balance, potassium levels, sodium levels, calcium effects, glucose concerns, uric acid concerns, and patient safety.
This article focuses specifically on thiazide diuretics. For the broader topic, including all major classes of diuretics, students should review the main pillar article first. Thiazides are only one part of the wider diuretic family, but they are important because they are frequently discussed in cardiovascular pharmacology, blood pressure management, and nursing medication safety.
This article is for nursing and healthcare education only. It does not replace clinical judgment, provider orders, institutional policy, or medication guidance from a licensed healthcare professional.
Need Help With Nursing Pharmacology?
Thiazide diuretics can be challenging because they connect kidney function, blood pressure control, electrolyte monitoring, medication safety, and patient education. If you are working on a nursing pharmacology assignment, medication analysis, care plan, or case study, our academic support team can help you organize your work clearly and safely.
Get expert help with your nursing pharmacology assignment today.
What Are Thiazide Diuretics?
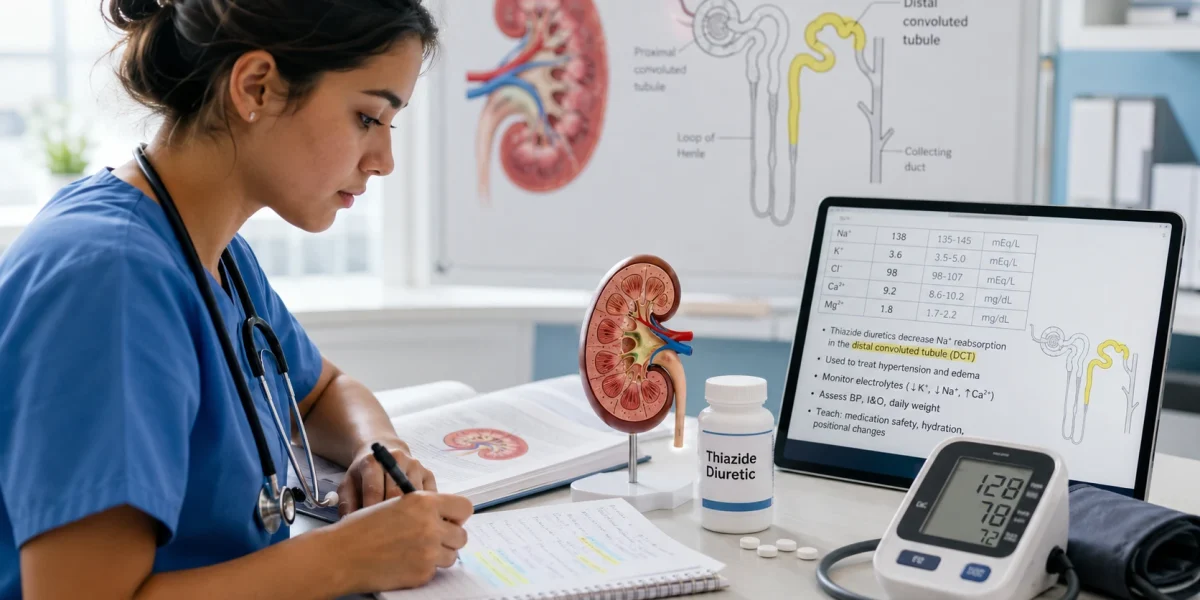
Thiazide diuretics are medications that increase urine output by reducing sodium and chloride reabsorption in the distal convoluted tubule of the nephron. They act on the sodium-chloride cotransporter, which helps move sodium and chloride from the tubular fluid back into the bloodstream. When this reabsorption is reduced, more sodium remains in the urine, and water follows sodium into the urine. This leads to increased sodium and water excretion (Patel, 2025).
Students should understand the difference between the broader term diuretics, the more specific term thiazide diuretics, and the related term thiazide-like diuretics. Diuretics include several medication classes, such as loop diuretics, potassium-sparing diuretics, osmotic diuretics, carbonic anhydrase inhibitors, and thiazides. Thiazide diuretics are one class within that larger group.
Thiazide-like diuretics are medications that have similar clinical effects to thiazides, although they may differ chemically or pharmacokinetically. Chlorthalidone, indapamide, and metolazone are commonly discussed as thiazide-like diuretics. Hydrochlorothiazide is one of the most recognized thiazide diuretics.
The patient-friendly term water pills is often used for diuretics, but students should use it carefully. Thiazides do increase urine output, but they also affect electrolytes, blood pressure, kidney response, glucose, uric acid, and patient safety. Calling them “water pills” can oversimplify the nursing assessment needed.
| Term | Meaning |
|---|---|
| Diuretics | Medications that increase urine output by affecting kidney handling of sodium, water, or electrolytes |
| Thiazide diuretics | Diuretics that act mainly in the distal convoluted tubule |
| Thiazide-like diuretics | Drugs with similar clinical effects to thiazides, often used in similar situations |
| Water pills | Common patient-friendly term for diuretics, although it oversimplifies their electrolyte effects |
How Thiazide Diuretics Work
Thiazide diuretics work in the nephron, the functional unit of the kidney. Each nephron filters blood, reabsorbs needed substances, and removes waste products or excess fluid. The nephron includes the glomerulus, proximal tubule, loop of Henle, distal convoluted tubule, and collecting duct.
Thiazides Act in the Distal Convoluted Tubule
Thiazides act mainly in the distal convoluted tubule. This location matters because each diuretic class works in a different nephron site. Loop diuretics act in the loop of Henle, while thiazides act farther along the nephron.
Hydrochlorothiazide inhibits the sodium-chloride cotransporter on the apical membrane of the distal convoluted tubule. This reduces sodium reabsorption at that site (Herman & Bashir, 2023).
The Sodium-Chloride Cotransporter
The sodium-chloride cotransporter normally helps move sodium and chloride from the tubular fluid back into the blood. When thiazides block this transporter, more sodium and chloride stay in the tubular fluid.
Water tends to follow sodium. As more sodium remains in the urine, more water leaves the body through urine. This explains why urine output may increase after thiazide use.
Blood Pressure Effects
Thiazides may help lower blood pressure by reducing sodium and fluid retention. Less retained sodium and water can reduce circulating fluid volume, which may support blood pressure control in selected patients.
Thiazides may also have longer-term vascular effects that contribute to blood pressure reduction. Students do not need to memorize every vascular mechanism, but they should remember that thiazides are important blood pressure medications, not only “water pills.”
Why Thiazides Are Usually Milder Than Loop Diuretics
Thiazides are usually less potent diuretics than loop diuretics because the distal convoluted tubule reabsorbs less sodium than the loop of Henle. However, less potent does not mean less important.
Thiazides can still have major clinical value in hypertension management and selected cases of mild fluid retention. Students should not judge a diuretic only by how strongly it increases urine output.
Electrolyte Effects
Thiazide action also explains the electrolyte concerns. When sodium delivery to later nephron segments increases, potassium handling may change. This can contribute to potassium loss in some patients.
Sodium loss and fluid shifts may also contribute to hyponatremia in susceptible patients. Thiazides may reduce urinary calcium loss, which makes their calcium effect different from loop diuretics.
| Mechanism Point | Student-Friendly Explanation |
|---|---|
| Site of action | Mainly distal convoluted tubule |
| Transporter affected | Sodium-chloride cotransporter |
| Main renal effect | More sodium and water leave in urine |
| Blood pressure effect | Reduced fluid volume and vascular effects may help lower blood pressure |
| Potassium concern | Potassium may decrease in some patients |
| Sodium concern | Sodium may decrease in some patients |
| Calcium effect | Thiazides may reduce urinary calcium loss |
Common Thiazide and Thiazide-Like Diuretics
Students should learn the class before memorizing individual drug names. Once the class is clear, each medication becomes easier to place. The most commonly discussed thiazide and thiazide-like medications include hydrochlorothiazide, chlorthalidone, indapamide, and metolazone.
Hydrochlorothiazide is commonly recognized as a thiazide diuretic. It is used for hypertension and peripheral edema and works by inhibiting sodium reabsorption in the distal convoluted tubule (Herman & Bashir, 2023).
Chlorthalidone is often described as a thiazide-like diuretic. It is frequently discussed in hypertension management and is known for a longer duration of action compared with hydrochlorothiazide. Indapamide is another thiazide-like diuretic used in some blood pressure management contexts. Metolazone is also thiazide-like and may be used in more complex fluid management situations under close monitoring.
Students should avoid assuming that all thiazide and thiazide-like medications are identical. They share similar mechanisms and clinical themes, but they may differ in duration, potency, clinical use patterns, and risk of electrolyte changes. StatPearls notes that electrolyte abnormalities with chronic thiazide therapy may occur particularly with longer-acting agents such as chlorthalidone and metolazone (Arumugham & Shahin, 2023).
A future or existing diuretic drugs list article can help students compare drug names across diuretic classes without making this thiazide article too broad.
| Drug | Type | Common Student Note |
|---|---|---|
| Hydrochlorothiazide | Thiazide diuretic | Commonly associated with hypertension and mild fluid retention |
| Chlorthalidone | Thiazide-like diuretic | Longer-acting option often discussed in hypertension management |
| Indapamide | Thiazide-like diuretic | Used in some blood pressure management contexts |
| Metolazone | Thiazide-like diuretic | Sometimes used in complex fluid management under close monitoring |
Why Are Thiazide Diuretics Used?
Thiazide diuretics may be prescribed for several reasons, but students should describe their uses safely. Nurses do not prescribe thiazides or independently change treatment. Nurses assess, monitor, administer medications as prescribed, educate patients, document findings, and report concerns according to policy.
Thiazide Diuretics for Hypertension
Thiazide and thiazide-like diuretics are commonly used in blood pressure management. They may help lower blood pressure by reducing sodium and fluid volume and through longer-term vascular effects. The 2025 American Heart Association and American College of Cardiology hypertension guideline discusses medication treatment for high blood pressure and includes diuretics among major antihypertensive medication classes (Writing Committee Members, 2025).
For nursing students, the key point is not to turn thiazides into a full hypertension guideline. The key point is to understand why thiazides appear in blood pressure medication discussions. When sodium and fluid volume decrease, blood pressure may improve in selected patients. However, the patient’s full cardiovascular risk, comorbidities, medication profile, and provider-directed plan guide therapy.
Students can review diuretics for hypertension, and cardiac medications for broader cardiovascular pharmacology learning.
Thiazide Diuretics for Mild Fluid Retention
Thiazides may also be prescribed for mild edema or fluid retention in selected patients. This may include peripheral edema or other fluid-related conditions depending on the cause and provider direction. Hydrochlorothiazide is approved for peripheral edema as well as hypertension (Herman & Bashir, 2023).
Students should avoid assuming that all edema is treated the same way. Edema can be related to heart failure, kidney disease, liver disease, venous disease, medications, or other causes. Thiazides may be appropriate in some contexts, while loop diuretics may be preferred in others. The provider diagnoses the cause and selects the treatment plan.
Students can review diuretics for edema for a focused discussion of fluid retention.
Other Uses Students May Encounter
Students may also encounter thiazides in discussions of calcium handling. Because thiazides may reduce urinary calcium loss, they may be discussed in selected calcium-related contexts under provider guidance. This does not mean students should recommend thiazides for calcium problems. It means they should recognize that thiazides have a calcium effect that differs from loop diuretics.
Thiazides may also appear in discussions about resistant hypertension, combination therapy, and medication selection in patients with comorbidities. These topics should be learned within provider-directed treatment frameworks, not as independent nursing treatment decisions.
Thiazide Diuretics and Electrolytes
Thiazide diuretics should not be remembered only as “water pills.” Their electrolyte effects are central to safe nursing care. Students should connect thiazides to potassium, sodium, calcium, glucose, uric acid, renal function, patient symptoms, and fall risk.
Electrolyte abnormalities are among the most important adverse effects associated with thiazide therapy. StatPearls notes that electrolyte abnormalities are the most common adverse effects associated with chronic thiazide therapy in hypertension (Arumugham & Shahin, 2023).
Thiazide Diuretics and Potassium
Thiazide diuretics may contribute to potassium loss and hypokalemia. Potassium is essential for muscle function, nerve signaling, and cardiac rhythm. When potassium becomes too low, a patient may experience weakness, fatigue, muscle cramps, or cardiac rhythm concerns depending on severity and clinical context.
The potassium effect occurs because thiazides increase sodium delivery to later nephron segments. This can increase potassium secretion in the distal nephron. Students do not need to memorize every renal exchange mechanism in detail, but they should remember this practical point: thiazides can lower potassium in some patients.
Nurses monitor potassium levels where ordered, assess symptoms, review clinical context, and report abnormal findings according to institutional policy. Students should also understand the difference between thiazides and potassium-sparing diuretics. Thiazides may lower potassium; potassium-sparing diuretics may increase potassium. Confusing these effects can lead to unsafe patient education.
Thiazide Diuretics and Sodium
Thiazide diuretics may contribute to hyponatremia in some patients. Hyponatremia means low sodium. Sodium is important for fluid balance, neurological function, and cellular stability. Low sodium may cause weakness, dizziness, headache, nausea, confusion, falls, or neurological changes depending on severity and patient context.
Thiazide-associated hyponatremia is a well-recognized medication safety concern. The MSD Manual explains that thiazide diuretics can decrease the kidney’s diluting capacity and increase sodium excretion, contributing to hyponatremia in susceptible patients (MSD Manual Professional Edition, n.d.).
For nursing students, the key point is to connect sodium changes with patient presentation. A patient who becomes confused, weak, dizzy, or unsteady while taking a thiazide may need assessment and escalation. Nurses do not diagnose hyponatremia independently, but they monitor ordered labs, assess symptoms, document changes, and report concerns.
Thiazide Diuretics and Calcium
Thiazides may reduce urinary calcium loss. This means more calcium may remain in the body compared with what happens when calcium excretion increases. This effect is one reason thiazides are discussed differently from loop diuretics in electrolyte teaching.
Students should not overstate this point. Thiazides may affect calcium balance, but the clinical meaning depends on the patient’s condition, labs, provider goals, and medication profile. In nursing practice, calcium monitoring may be relevant where ordered or where the patient has calcium-related concerns.
This is also a useful memory distinction: loop diuretics may increase calcium excretion, while thiazides may reduce urinary calcium loss. This difference helps students avoid treating all diuretics as if they have the same electrolyte pattern.
Thiazide Diuretics, Glucose, and Uric Acid
Thiazide diuretics may be associated with glucose-related changes and increased uric acid in some patients. Merck Manual lists glucose intolerance, hyperuricemia, hypercalcemia, and hypokalemia among selected adverse effects of thiazide and thiazide-like diuretics (Merck Manual Professional Edition, n.d.).
Glucose concerns may matter in patients with diabetes or metabolic risk. This does not mean thiazides are automatically inappropriate for patients with diabetes. It means students should understand why glucose may be monitored in some patients and why providers consider the full clinical picture.
Uric acid concerns may matter in patients with gout history or gout risk. Increased uric acid can contribute to gout flares in susceptible patients. Nurses should not tell patients to stop medication because of gout concerns, but they should encourage patients to report symptoms and discuss concerns with their healthcare provider.
| Parameter | Why It Matters With Thiazide Diuretics |
|---|---|
| Potassium | Low potassium may affect muscles and cardiac rhythm |
| Sodium | Low sodium may affect neurological status and safety |
| Calcium | Thiazides may reduce urinary calcium loss |
| Glucose | Some patients may need monitoring where clinically relevant |
| Uric acid | Increased uric acid may matter in patients with gout risk |
| Blood pressure | Hypotension or dizziness may occur in some patients |
| Renal function | Kidney response and medication safety may require monitoring |
Thiazide Diuretics Side Effects
Thiazide diuretics side effects vary by medication, dose, patient condition, hydration status, kidney function, age, and other medications. Some patients tolerate thiazides well, while others may develop clinically important changes that require monitoring and provider review.
Increased urination is an expected effect. However, frequent urination can affect comfort, sleep, toileting needs, and fall risk. Dizziness or lightheadedness may occur if blood pressure drops or if fluid volume becomes too low. Patients should report dizziness, fainting, severe weakness, confusion, muscle cramps, palpitations, or unusual symptoms.
Hypokalemia and hyponatremia are two important electrolyte concerns. Hypokalemia may affect muscle and cardiac function. Hyponatremia may affect neurological status and fall risk. Dehydration may affect blood pressure, renal perfusion, and overall safety.
Thiazides may also be associated with increased uric acid, glucose-related changes, renal function changes, photosensitivity where relevant, and general electrolyte imbalance. Merck Manual’s professional table lists hypokalemia, hyperuricemia, glucose intolerance, hypercalcemia, weakness, and rash among selected adverse effects for thiazide and thiazide-like diuretics.
| Possible Side Effect | Nursing or Student Relevance |
|---|---|
| Increased urination | Expected effect but may affect comfort and safety |
| Dizziness | May indicate blood pressure or fluid-volume changes |
| Hypokalemia | Important cardiac and muscle safety concern |
| Hyponatremia | May affect neurological function and fall risk |
| Dehydration | May affect blood pressure and renal perfusion |
| Increased uric acid | Important in patients with gout risk |
| Glucose changes | Relevant in patients with diabetes or metabolic risk |
| Photosensitivity | Patient teaching may be needed where applicable |
| Renal function changes | May require provider review and lab monitoring |
Nursing Considerations for Thiazide Diuretics
Nursing considerations for thiazide diuretics should be specific, practical, and safety-focused. Nurses administer thiazides as prescribed and monitor the patient’s response according to provider orders and institutional policy. Providers diagnose, prescribe, and adjust treatment plans.
Before Giving Thiazide Diuretics
Before giving a thiazide diuretic, nurses may review the medication order, patient identity, allergies, recent blood pressure, medication parameters, recent laboratory values where available, renal function results where clinically indicated, and the reason the medication was prescribed.
The nursing focus differs depending on whether the thiazide is being used for hypertension, mild fluid retention, or another provider-directed purpose. This helps the nurse know whether to focus mainly on blood pressure response, fluid status, symptoms, or ordered lab monitoring.
Blood Pressure and Fall-Risk Monitoring
Blood pressure monitoring is important because thiazides may lower blood pressure. Nurses should follow the medication order and institutional policy when checking blood pressure or assessing symptoms such as dizziness, lightheadedness, weakness, or orthostatic changes.
If a patient reports dizziness or appears unsteady, fall-risk precautions may be needed according to policy. This is especially important for older adults, patients with weakness, patients with frequent urination, and patients who are already at risk of falls.
Electrolyte Monitoring
Electrolyte monitoring is central to thiazide safety. Nurses may monitor potassium and sodium levels where ordered. Thiazides may contribute to hypokalemia or hyponatremia in some patients.
Nurses should also assess for symptoms that may suggest fluid or electrolyte concerns, such as muscle cramps, weakness, confusion, headache, dizziness, palpitations, or fainting. These symptoms do not automatically confirm an electrolyte problem, but they should prompt careful assessment and reporting when concerning.
Renal Function and Fluid Status
Renal function may need review depending on the patient and clinical setting. Thiazides act through the kidney, and kidney response affects medication safety. Patients with kidney disease, dehydration risk, older age, complex medication regimens, or acute illness may need closer monitoring.
If a thiazide is used for fluid retention, nurses may monitor edema, weight trends where ordered, intake and output when relevant, lung sounds, shortness of breath, and patient-reported swelling.
Medication Profile Review
Medication profile review is important within nursing scope. A patient may take multiple medications that affect blood pressure, electrolytes, renal function, glucose, uric acid, or hydration.
Nurses do not independently change therapy. However, they can identify concerns, document findings, and report possible issues to the healthcare team according to institutional policy.
Documentation and Reporting
Documentation should include medication administration, relevant assessment findings, blood pressure response, symptoms, education provided, intake and output or weight data where ordered, abnormal findings, and provider notification when required.
Students can review diuretics nursing considerations for broader diuretic-monitoring principles.
Patient Education for Thiazide Diuretics
Patient education for thiazide diuretics should be clear, safe, and practical. Nurses should teach within scope and according to provider instructions. Patients should take thiazide medications exactly as prescribed and should not stop taking them without speaking to a healthcare provider.
Patients should understand that increased urination may occur. If frequent urination disrupts sleep or daily activities, patients should ask the provider or pharmacist about medication timing. Nurses should avoid giving independent timing changes unless those instructions are part of the prescribed plan or institutional guidance.
Patients should be taught to rise slowly if dizziness occurs and to use fall-prevention strategies when appropriate. Dizziness, fainting, severe weakness, confusion, muscle cramps, palpitations, or unusual symptoms should be reported. These symptoms may relate to blood pressure changes, dehydration, electrolyte imbalance, or other clinical concerns.
Follow-up appointments and laboratory tests are important when ordered. Patients may need monitoring of blood pressure, potassium, sodium, renal function, glucose, or uric acid depending on the medication and patient condition. Those with diabetes, gout history, kidney disease, pregnancy-related concerns, or multiple medications should discuss these issues with their healthcare provider.
Patients should follow provider instructions about sodium, potassium, fluids, and diet. They should not independently increase potassium intake, restrict sodium, change fluid intake, start supplements, or use herbal products without professional guidance. This is especially important because electrolyte needs differ from patient to patient.
Patients should also be cautious with over-the-counter medications and supplements. Some products can affect blood pressure, kidney function, hydration, or electrolyte balance. Nurses can encourage patients to ask a provider or pharmacist before starting new products.
Thiazide vs Loop Diuretics
Thiazide and loop diuretics both increase sodium and water excretion, but they work in different nephron sites. Thiazides act mainly in the distal convoluted tubule, while loop diuretics act in the loop of Henle. Loop diuretics are often stronger and are commonly associated with fluid overload, edema, and heart failure-related congestion. Thiazides are commonly associated with hypertension and mild fluid retention.
For a fuller comparison, students can review loop vs thiazide diuretics and loop diuretics.
| Feature | Thiazide Diuretics | Loop Diuretics |
|---|---|---|
| Main site of action | Distal convoluted tubule | Loop of Henle |
| Common examples | Hydrochlorothiazide, chlorthalidone | Furosemide, bumetanide, torsemide |
| Typical diuretic strength | Usually milder | Often stronger |
| Common association | Hypertension, mild fluid retention | Edema, heart failure-related fluid overload |
| Potassium concern | May lower potassium | May lower potassium |
| Student memory point | Common blood pressure diuretic class | Stronger fluid-removal class |
Study Tips for Thiazide Diuretics
Students should learn thiazide diuretics by class before memorizing drug names. The class tells you where the medication works, what it does, what electrolyte problems may occur, and what nursing monitoring is important.
First, connect thiazides to the distal convoluted tubule. Second, remember the sodium-chloride cotransporter. Third, connect reduced sodium-chloride reabsorption with increased sodium and water excretion. Fourth, connect thiazides with hypertension and mild fluid retention. Fifth, monitor potassium, sodium, renal function, blood pressure, and patient symptoms.
Students should also remember the calcium effect. Thiazides may reduce urinary calcium loss, which makes their calcium pattern different from loop diuretics. This can help students answer exam questions that compare diuretic classes.
Practice patient education scenarios. For example, if a patient says, “I feel dizzy after taking my water pill,” students should think about blood pressure, hydration, fall risk, electrolyte concerns, and the need to report concerning symptoms. If a patient asks whether they should change potassium intake, the safe answer is that they should follow provider instructions and speak with the healthcare team before changing diet, supplements, or medications.
Student memory point: Thiazide diuretics act in the distal convoluted tubule, are commonly associated with hypertension management, and require monitoring of blood pressure, potassium, sodium, renal function, and patient symptoms.
Common Mistakes Students Make With Thiazide Diuretics
One common mistake is thinking thiazides and loop diuretics are the same. They are both diuretics, but they act in different nephron sites and are commonly associated with different clinical priorities.
Another mistake is forgetting that thiazides act in the distal convoluted tubule. This detail helps students remember the sodium-chloride cotransporter and the electrolyte effects.
Some students memorize hydrochlorothiazide without understanding the class. Drug names are easier to remember when students first understand the mechanism.
Another common error is ignoring sodium and potassium monitoring. Thiazides may contribute to hypokalemia and hyponatremia, and both can affect patient safety.
Students may also forget glucose and uric acid considerations. These issues matter in patients with diabetes risk, metabolic concerns, or gout history.
Another mistake is assuming increased urination is the only important effect. Thiazides can affect blood pressure, fluid volume, electrolytes, renal function, calcium handling, glucose, and uric acid.
Students may also give unsafe patient advice about potassium, sodium, fluids, supplements, or herbal products. Patients should follow provider instructions and speak with a healthcare professional before making changes.
Finally, students sometimes confuse thiazide and potassium-sparing electrolyte effects. Thiazides may lower potassium; potassium-sparing diuretics may increase potassium.
Summary: What Students Should Remember About Thiazide Diuretics
Thiazide diuretics are a major diuretic class. They act mainly in the distal convoluted tubule by reducing sodium-chloride reabsorption. This increases sodium and water excretion and may help lower blood pressure or manage mild fluid retention in selected patients when prescribed.
Common examples include hydrochlorothiazide, chlorthalidone, indapamide, and metolazone. Hydrochlorothiazide is commonly recognized as a thiazide diuretic, while chlorthalidone, indapamide, and metolazone are often described as thiazide-like diuretics.
Important monitoring includes blood pressure, potassium, sodium, renal function, dizziness, weakness, dehydration symptoms, glucose concerns, and uric acid concerns where clinically relevant. Patient education should emphasize prescribed use, follow-up labs, symptom reporting, fall prevention, and avoiding independent changes to medications, diet, fluid intake, supplements, or herbal products.
For nursing students, thiazide diuretics are best learned through class, nephron site, mechanism, examples, electrolyte effects, side effects, nursing monitoring, and safe patient teaching.
Need Help Understanding Thiazide Diuretics?
Thiazide diuretics can be difficult to master because they involve the distal convoluted tubule, sodium-chloride reabsorption, potassium loss, hyponatremia risk, blood pressure monitoring, and patient teaching. If you need help with a nursing assignment, care plan, case study, medication analysis, or pharmacology paper, our nursing academic support team can help you develop a clear, evidence-based, and well-organized response.
Need help with your nursing assignment? Contact us today for professional nursing academic support.
Frequently Asked Questions About Thiazide Diuretics
What are thiazide diuretics?
Thiazide diuretics are medications that increase urine output by reducing sodium and chloride reabsorption in the distal convoluted tubule of the nephron. They are commonly associated with hypertension management and mild fluid retention. They are sometimes called water pills, but that term oversimplifies their effects on electrolytes, blood pressure, renal function, and patient safety.
What are examples of thiazide diuretics?
Hydrochlorothiazide is a common thiazide diuretic. Chlorthalidone, indapamide, and metolazone are commonly described as thiazide-like diuretics because they have similar clinical effects. Students should learn the class first, then connect each drug name to its mechanism, common use, electrolyte risks, and nursing monitoring priorities.
Is hydrochlorothiazide a thiazide diuretic?
Yes. Hydrochlorothiazide is a thiazide diuretic. It works in the distal convoluted tubule by inhibiting sodium reabsorption through the sodium-chloride cotransporter. It is commonly associated with hypertension and peripheral edema management when prescribed (Herman & Bashir, 2023).
What are thiazide diuretics used for?
Thiazide diuretics may be prescribed for hypertension and mild fluid retention. Some thiazide-like drugs may also appear in more complex fluid management contexts under close monitoring. The exact reason depends on the patient’s condition, provider assessment, renal function, medication profile, and treatment plan.
How do thiazide diuretics work?
Thiazide diuretics work by inhibiting the sodium-chloride cotransporter in the distal convoluted tubule. This reduces sodium and chloride reabsorption, allowing more sodium and water to leave in urine. This can increase urine output and may help lower blood pressure in selected patients.
Where do thiazide diuretics work in the nephron?
Thiazide diuretics work mainly in the distal convoluted tubule. This is different from loop diuretics, which act in the loop of Henle. Knowing the nephron site helps students remember the mechanism, clinical uses, and electrolyte concerns.
Do thiazide diuretics lower potassium?
Thiazide diuretics may lower potassium in some patients and contribute to hypokalemia. Low potassium may affect muscle function and cardiac rhythm. Nurses monitor potassium where ordered, assess symptoms such as weakness or cramps, and report concerning findings according to policy.
Can thiazide diuretics cause low sodium?
Yes. Thiazide diuretics may contribute to hyponatremia in some patients. Low sodium can affect neurological status and may be associated with confusion, weakness, dizziness, headache, or falls depending on severity. Nurses monitor ordered labs and assess patient symptoms.
What should nurses monitor with thiazide diuretics?
Nurses may monitor blood pressure, dizziness, orthostatic symptoms, potassium, sodium, renal function, intake and output where relevant, edema where relevant, weakness, cramps, confusion, dehydration symptoms, glucose concerns, uric acid concerns, and fall risk. Monitoring should follow provider orders and institutional policy.
What is the difference between thiazide and loop diuretics?
Thiazide diuretics act mainly in the distal convoluted tubule and are commonly associated with hypertension and mild fluid retention. Loop diuretics act in the loop of Henle and are often stronger, commonly associated with edema and heart failure-related fluid overload. Both may affect potassium, but their usual clinical roles differ.
References
American Heart Association. (2025). 2025 AHA/ACC/AANP/AAPA/ABC/ACCP/ACPM/AGS/AMA/ASH/ASPC/NMA/PCNA guideline for the prevention, detection, evaluation, and management of high blood pressure in adults. Circulation. https://www.ahajournals.org/doi/10.1161/CIR.0000000000001356
Arumugham, V. B., & Shahin, M. H. (2023). Therapeutic uses of diuretic agents. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK557838/
Herman, L. L., & Bashir, K. (2023). Hydrochlorothiazide. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK430766/
Merck Manual Professional Edition. (n.d.). Oral diuretics for hypertension. Retrieved May 27, 2026, from https://www.merckmanuals.com/professional/multimedia/table/oral-diuretics-for-hypertension
MSD Manual Professional Edition. (n.d.). Hyponatremia. Retrieved May 27, 2026, from https://www.msdmanuals.com/professional/nephrology/electrolyte-disorders/hyponatremia
Patel, P. (2025). Thiazide diuretics. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK532918/
